
Health

When you need care, can you get it?

Can you afford visits to the GP? Get a health appointment when needed? See a specialist? Receive treatment in time? Each step matters—and improving one part of the system needs the people and services to make it work.

New Zealand has strengths in health outcomes, alongside barriers to getting care. This page brings together official evidence, findings from our analysis of 6,164 health headlines, and seven parties’ proposals to ask: what would make care easier to get, and how would we know it was improving?

Official statistics, media coverage and party proposals answer different questions. Their sources, dates and limitations are identified below.

Where does access break down?

A lower fee helps only if you can get an appointment. A referral helps only if it leads to the assessment or treatment you need. These are the points where policy promises meet patients’ experience.

Can you afford GP visits?

14.9% of adults

About one in seven adults reported that cost prevented a GP visit in the previous 12 months.

The policy test: Who would pay less, and would the change cover people who need frequent care?

Source: New Zealand Health Survey 2024/25.

Can you get an appointment?

25.5% of adults

About one in four adults reported that the time taken to get an appointment prevented a GP visit.

The policy test: Who will provide the extra appointments, where, and how soon?

Source: New Zealand Health Survey 2024/25.

Who reaches the waiting list?

A declined referral can leave someone outside the count.

Some patients are referred by their GP but are not accepted for a specialist appointment. They therefore do not appear on that waiting list. To understand access to care, we need to know both how long accepted patients wait and how many people needing specialist care cannot get onto the list.

The policy test: Are more people getting timely assessment and treatment—including those previously unable to reach the list?

Source: Social Herds health media report. The report examines news stories about declined referrals; it does not provide a national count.

Who faces the greatest barriers?

Access is unequal.

Cost prevented a GP visit for 18.7% of Māori adults and 25.1% of Pacific adults, compared with 14.9% of adults overall.

The policy test: Will improvements reach the people facing the greatest barriers, and will the gaps narrow?

Source: New Zealand Health Survey 2024/25.

The survey percentages describe adults reporting barriers during the previous 12 months. They are not counts of people currently waiting for treatment.
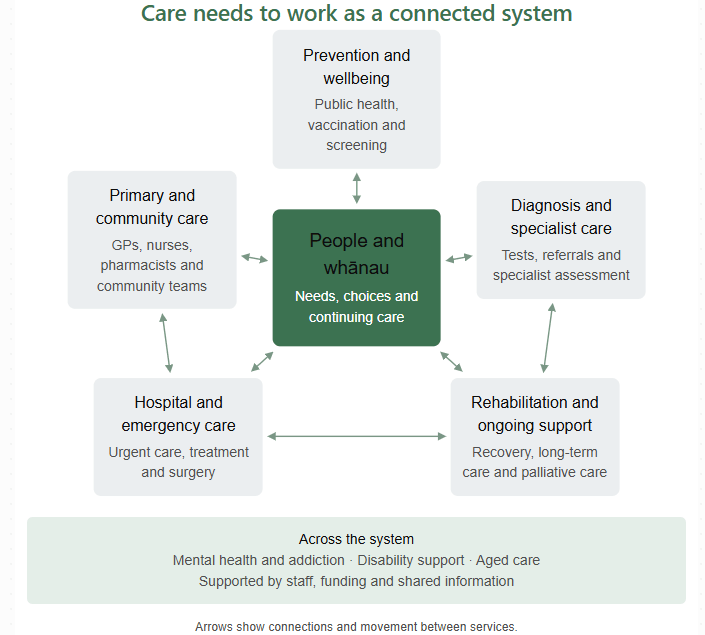
What happens before—and after—hospital?

Hospital pressure begins well before someone arrives at the emergency department. Affordable primary care, timely diagnosis and specialist access all matter. So does support that promotes recovery after leaving hospital.

What would the parties change—and could they deliver it?

Compare the proposals against the same practical questions: who benefits, what changes in their care, who provides it, how it is funded and when it happens.

The table identifies where proposals respond to the problems discussed here and what still needs testing. It covers the proposals summarised for this page; it is not a complete account of every party’s health programme. Campaign commitments and standing policies may differ in detail and readiness for delivery.

On a small screen: swipe across the table to read all four columns.

PartyWhat it proposesWhere it responds to the needWhat needs testing
National
  • A further $604 million for Pharmac, financed by reducing foreign aid outside the Pacific.
  • More clinical trials and locally produced CAR-T treatment.
  • Bowel screening from age 50.
  • Breast screening extended to 74 by 2029.
  • Free cervical screening for ages 25–69 from March 2027.

Source: National Party.

Connects earlier detection with treatment access. Specified screening dates and a medicines allocation provide commitments that can be tracked.Will diagnostic and treatment capacity keep up? Expanded screening needs staff, investigations and treatment places. Assess this package alongside plans for GP affordability, workforce retention and recovery support. Track access for people whose referrals are declined as well as those accepted onto lists.
Labour
  • Three free doctor visits annually.
  • Removal of the $5 prescription charge from July 2027.
  • Free cervical screening and maternity scans.
  • Loans supporting GP practice ownership.
  • A job guarantee for eligible New Zealand-trained graduate nurses from 2027.

Source: Labour Party.

Addresses financial barriers directly. GP ownership support and the graduate-nurse guarantee also recognise the workforce needed to provide care.Will a free visit also be an available visit? Delivery needs additional staffed appointments, graduate supervision and retention, and rural access. Three free visits may offer limited protection to people needing frequent care.
Green Party
  • Work towards fully free, publicly delivered primary and dental care.
  • Rural mobile clinics and diagnostics.
  • Increased Pharmac funding and expanded pharmacy services.
  • Primary-care nurse pay parity and safe staffing levels.
  • Stronger Māori health provision and health data infrastructure.

Source: Green Party of Aotearoa New Zealand.

Addresses connected pressures: affordability, prevention, rural access, workforce conditions and Māori health inequities.Which services become free first, and when? The reviewed health chapter does not establish complete costs or delivery stages. Test the timetable, clinician training and retention, and funding for safe staffing.
ACT
  • Increase the medicines share of the health budget towards Australian parity by 2033, using future budget growth.
  • Expand pharmacists’ treatment and monitoring roles.
  • Establish National Cancer Centre campuses in Auckland and Christchurch using public investment, private capital and philanthropy.

Source: ACT New Zealand.

Expanded pharmacy services could ease GP appointment pressure. Medicines investment and coordinated cancer services address treatment access.How will these services work for patients across the country? Pharmacy care needs clear fees, training, shared records and referrals. Cancer centres need operating funds, specialists and travel support. Increased medicines spending must be considered alongside other services’ rising demand.
New Zealand First
  • An initial health campaign package focused on prevention and metabolic health.
  • Nutrition education, reduced GP administration and health coaches.
  • Research into nutritional interventions, vitamin D and intravenous vitamin C around surgery.

Source: New Zealand First.

Recognises prevention and primary-care administrative burdens. Health coaches could support long-term conditions if integrated effectively with clinical services.What measurable improvement in access would this deliver? The initial package gives limited detail on GP affordability, staffing numbers, specialist access or waiting times. Research proposals require evaluation; their clinical benefits should not be assumed. Funding and service commitments need clearer specification.
Te Pāti Māori
  • Rebuild and strengthen Māori-led health authority and services.
  • Prioritise prevention and whānau wellbeing.
  • Make care accessible, culturally safe and accountable to Māori.

Source: Te Pāti Māori public summary.

Addresses unequal access and whether services meet Māori needs. Whānau wellbeing supports care beyond hospital treatment.How will the approach translate into accessible services? Assess funding, workforce commitments, dates and outcomes, plus connections between Māori-led services, primary care, hospitals and recovery support. This assessment is limited to the public summary; the full linked policy was not verified in the page review.
Opportunity Party
  • A cross-party, ten-year health plan.
  • A gradual increase in public health funding towards 9% of GDP.
  • Greater emphasis on primary and preventive care.
  • Stable Māori-provider commissioning, measurable equity goals and public reporting.

Source: The Opportunity Party.

Addresses continuity, repeated restructuring and the link between plans and delivery. Long-term funding and public milestones could make progress easier to assess.How would political agreement become staffed services? Delivery needs a credible funding path, regional improvements and patient outcomes. The 9% proposal concerns public funding and should not be directly compared with total public-and-private expenditure figures.

These summaries retain the policy material from the existing Health page. Policies can change during the campaign. Where detail was not established in the material reviewed, that is a limit of this assessment rather than proof that no further detail exists.

What does the media coverage add?

Our report examines 6,164 health headlines from 130 outlets to explore how access, staffing and delivery were covered. One issue it brings into focus is the difference between reporting waiting-time results and understanding the experience of people who never reach a specialist list.

Our understanding of New Zealand’s health system draws on both media coverage and official evidence. Media highlight concerns about access, staffing and delivery, while official statistics and research help establish the scale of those problems and whether conditions are improving. Reading them together helps us assess whether proposed solutions address people’s needs.

Read the evidence behind this page

Why do good health outcomes not mean everyone can get care?

Population outcomes and access measure different things. Life expectancy reflects wider living conditions as well as health care. Treatment results tell us about selected patients who received care. Neither measure alone tells us whether everyone needing help can get it.

82 years of life expectancy

New Zealand’s life expectancy was 82 years in 2023, 0.9 years above the OECD average. That is a strength—but it does not remove the need to examine cost, appointment delays and access to treatment.

Commonwealth Fund: strong outcomes, weak equity

  • In Mirror 2024, New Zealand ranked fourth overall among ten countries, third for health outcomes and first for care process, which covers prevention, safety, coordination and patients’ experiences of care.
  • It ranked eighth of nine for equity, ahead of only the United States; Sweden was excluded from that category. Income-related differences in access and care experiences contributed to this result.
  • This is a comparison of selected countries, not a world ranking. It draws on surveys from 2021–2023 and other data. Some New Zealand mortality figures were preliminary and underestimated preventable and treatable deaths.

Source: Commonwealth Fund, Mirror, Mirror 2024

OECD: strengths in selected treatments, fewer hospital beds

  • The OECD’s Health at a Glance 2025 reports 30-day mortality after a heart attack of 4.6% in New Zealand, compared with 6.5% across the OECD. After stroke, the figures were 6.7% and 7.7%. These indicators use unlinked hospital data and cover selected conditions.
  • New Zealand had 2.5 hospital beds per 1,000 people, compared with an OECD average of 4.2. Bed numbers need to be considered alongside staffing, demand and care available outside hospital.

Missing New Zealand data limits international comparisons

  • The OECD’s country note states that New Zealand lacks figures to compare unmet healthcare needs, avoidable admissions, and preventable and treatable mortality with other countries. Local evidence may still exist, but these gaps limit the international comparison.
  • Source: OECD, Health at a Glance 2025 — New Zealand country note

These publications use different measures and reference years. They provide context rather than a single assessment of current health-system performance.

What would improvement look like?

  • More people able to afford care.
  • Appointments available when needed.
  • Timely diagnosis and treatment.
  • Fewer people left outside the measures.
  • Narrower gaps between communities.

Ask every party:

  • What will change for patients,
  • who will deliver it,
  • when will it happen—and
  • what evidence will show it has worked?

Return to the party comparison ↑

Historical health comparisons

The earlier material below is retained for historical context. Its dates refer to previous publications and data, rather than current performance.

Health status indicators — 2016 data

OECD — Health status data

The five indicators used to compare health status are:

  • Male life expectancy at birth (2016).
  • Female life expectancy at birth (2016).
  • Survival to age 65 for males (2016).
  • Survival to age 65 for females (2016).
  • Under-age-five mortality per 1,000 live births (2016).

Stats NZ health expectancy — material published in 2014

NZ Progress Indicators — Statistics New Zealand

  • Between 1996 and 2006, health expectancy at birth increased 1.7 years for females and 2.7 years for males.
  • Female health expectancy increased from 67.5 to 69.2 years.
  • Male health expectancy increased from 64.7 to 67.4 years, with the gender gap closing most rapidly between 2001 and 2006.
  • Changes in health expectancy occur over long timeframes.

OECD Better Life Index — 2013

Historical health risk indicators

Smoking: New Zealand’s rate was below the OECD average of 20.9%.

Obesity: New Zealand’s rate was 27.8%, compared with the OECD’s 17.2%.

Historical health expenditure

  • Health spending was estimated at 10.3% of GDP, compared with an OECD average of 9.4%.
  • Total spending per person was USD 3,182 in 2011, below the OECD average of USD 3,322.
  • Between 2000 and 2010, real health spending grew by an annual average of 5.1% in New Zealand, compared with 4.0% across the OECD.
  • New Zealand’s growth slowed to less than 2.0% between 2010 and 2011.